
Menu
-
Shop All
Contact
hey@getstride.com
Stride Health Group
Stride Health Group Ltd
Company No 05158025
Lamas Road
Badersfield
Norwich
England
NR10 5FB
UK








News
8 Minutes
Why ApoB is changing heart risk assessment
Cholesterol tests measure how much cholesterol your blood carries. ApoB counts the particles carrying it, and that can reveal heart risk LDL misses.

 14/02/2026
Old way vs new way of measuring cholesterol
Most people are told they have “high cholesterol” without much explanation of what that means or why it matters. In reality, cholesterol and the particles that carry it are not the same thing, and that distinction is why newer markers like ApoB are now measured alongside traditional cholesterol tests.
This article explains:
First, what is cholesterol?
Cholesterol is a fat-like molecule your body can't do without. It is used to:
Build cell membranes
Produce steroid hormones
Make vitamin D
Make bile acids for digestion
Your liver makes most of the cholesterol you need. Some also comes from food.
Cholesterol is not harmful by default. Problems start when it ends up in the wrong place, particularly inside artery walls.
What is a lipoprotein, and why do we need them?
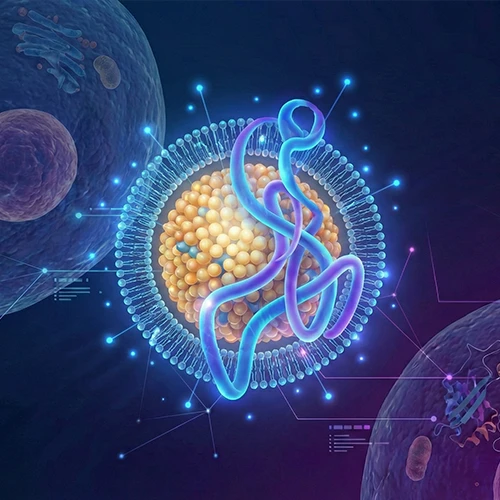
Blood is mostly water, and cholesterol and fats don't dissolve in water. To move cholesterol safely through the bloodstream, the body packages it into lipoproteins: microscopic transport particles made of fat and protein.
Think of it like this:
Cholesterol is the cargo
Lipoproteins are the vehicles (or boats)
Different lipoproteins carry cholesterol in different directions and behave differently in the circulation. That's why cholesterol testing is really about lipoproteins, not cholesterol alone.
The old way: traditional cholesterol markers
The traditional lipid panel looks at how much cholesterol is being carried, rather than how many particles are carrying it. These tests are still the backbone of NHS cardiovascular risk assessment.
Total cholesterol
Total cholesterol is the combined amount of cholesterol carried by all lipoproteins. It's useful for screening, but it doesn't show how cholesterol is split between protective and harmful particles.
LDL cholesterol (LDL-C)
LDL cholesterol reflects how much cholesterol is carried inside low-density lipoprotein particles. It is a central target in UK and European guidelines, it is strongly associated with cardiovascular events, and it responds well to lifestyle changes and statins.
Its limitation is that it measures cholesterol mass, not particle number.
HDL cholesterol (HDL-C)
HDL cholesterol measures cholesterol carried by high-density lipoproteins, which help remove excess cholesterol from artery walls. Higher HDL is generally associated with lower risk, but HDL function matters as much as the amount, and very high HDL isn't always protective.
HDL % of total cholesterol
This calculated marker shows how much of your total cholesterol comes from HDL. It gives a simple view of lipid balance and can highlight an unfavourable pattern even when total cholesterol looks acceptable.
The limitation of the old way
Two people can have the same LDL cholesterol and very different cardiovascular risk. LDL-C tells you how much cholesterol is inside LDL particles. It doesn't tell you how many LDL-like particles are circulating, and more particles means more chances for cholesterol to get into artery walls over the years.
This gap matters most in people with:
Insulin resistance or metabolic syndrome
High triglycerides
Fatty liver disease
A strong family history of early heart disease
The new way: ApoB and particle counting
What ApoB measures
Apolipoprotein B (ApoB) is a structural protein found on every atherogenic lipoprotein: LDL, VLDL, IDL and lipoprotein(a). Each of these particles carries exactly one ApoB molecule.
That makes ApoB a direct count of the particles that can drive plaque, rather than a measure of how much cholesterol they contain. LDL cholesterol tells you how much cargo is being carried. ApoB tells you how many boats are on the river.
Why ApoB matters
Cardiovascular risk is driven by how often artery walls are exposed to atherogenic particles over time. Large genetic studies, population cohorts and meta-analyses consistently show that:
ApoB predicts cardiovascular events at least as well as LDL-C, and often better
Lowering ApoB lowers the risk of heart attack and stroke
LDL-C and ApoB can disagree, and when they do, ApoB can reveal risk that LDL-C misses
Many preventive cardiologists now use this particle-based view, focusing on cumulative lifetime exposure rather than short-term thresholds.
A real example: ApoB in someone who felt fine
Stride founder Andrew Steele spent most of his adult life as an Olympic athlete, where training and nutrition were part of the job. By his forties, life looked different: two children, a move of house and country, a start-up to build, less training and more stress. He felt fine. His blood results said otherwise.
His first panel showed a CRP (an inflammation marker) of 1.39, higher than he expected, along with raised LDL cholesterol, an ApoB level he wasn't comfortable with and folate below the optimal range. LDL and ApoB were both up, which suggested an early pattern rather than a one-off lab quirk.
He kept the changes deliberately simple:
Running twice a week instead of once. Regular aerobic exercise improves insulin sensitivity and how the body handles triglycerides, which affects how many ApoB-carrying particles the liver releases.
Adding fibre to meals. Rather than cutting foods out, he added fibre, which helps the body clear cholesterol and steadies triglycerides after eating.
Eating more protein. This helped with appetite, steadier energy and glucose control (more on that in nutrition by addition).
Addressing low folate with a methylated B vitamin.
Three months later he retested. His inflammation marker had dropped, folate had improved, ApoB had come down and LDL cholesterol was trending down. He couldn't have felt any of those changes. Without retesting, there was no way to know whether the new habits were working.
This profile is common in people who are over 40, train less than they used to and carry more mental load, while still looking healthy from the outside. You can't feel particle number or low-grade inflammation, which is why measuring them is useful.
Old way vs new way: comparison table
| Marker | What it measures | What it tells you | Main limitation |
|---|---|---|---|
| Total cholesterol | Cholesterol content | Broad screening | No particle insight |
| LDL-C | Cholesterol in LDL | Treatment guidance | Misses particle count |
| HDL-C | Cholesterol in HDL | Protective context | Function not measured |
| HDL % | Balance of cholesterol | Ratio insight | Still cholesterol-based |
| ApoB | Particle number | Atherogenic particle burden | Less widely ordered |
NHS perspective vs modern prevention
The NHS approach prioritises cost-effective population screening, LDL-C and non-HDL cholesterol, and risk calculators to guide treatment. That works well for most people.
Preventive cardiology adds another question: how many atherogenic particles has this person been exposed to over a lifetime? ApoB helps answer it, especially when standard cholesterol tests underestimate risk.
This isn't a replacement model. The strongest assessments combine LDL-C, non-HDL cholesterol, ApoB, inflammatory markers and metabolic context.
FAQs
Is cholesterol itself bad?
No. Cholesterol is essential. Risk depends on where it ends up and how often artery walls are exposed to cholesterol-carrying particles.
Is LDL cholesterol outdated?
No. LDL-C remains clinically useful. ApoB adds precision rather than replacing it.
Can ApoB be high when LDL looks normal?
Yes. It's common with insulin resistance and high triglycerides, and it can signal higher risk than LDL alone suggests.
Can you lower ApoB with lifestyle changes?
Often, yes. Regular exercise, more fibre, less saturated fat and better blood sugar control can all bring ApoB down. Some people also need medication, so discuss your results with your GP.
Should everyone measure ApoB?
Not necessarily. ApoB is most helpful when risk is unclear or underestimated, or when you want to check that changes or treatment are working.
The bottom line
Cholesterol is the cargo and lipoproteins are the vehicles. Traditional tests measure how much cholesterol is being carried; ApoB counts how many vehicles are on the road.
Used together, these markers give a clearer, more personal picture of cardiovascular risk without abandoning the evidence behind NHS care. If you want to see your own ApoB alongside LDL, HDL and Lp(a), Optimal Bloods measures them from an at-home blood draw.
Find out what your body is actually trying to tell you.
Answer 8 quick questions and get a free personalised report - covering which area of your biology is most worth looking at first, what testing in that area reveals, and what actions become available once you have that data.
Where do you feel you're operating below your potential right now?
Methylation & Cellular Health
Your biology is signalling a methylation upgrade - here’s what that means and what to do about it.